• Home
  • RSS
  • Contact
POWERED BY
Showing posts with label HEALTH CARE. Show all posts

Why women suffer more than men from icy toes... and what we can do about it

cold feet

Women are up to nine times more likely to suffer from cold hands and feet than men, I read last week. We feel changes in temperature and the seasonal chill more. Did this surprise me? Not a bit.

I am always moaning about how bitter the weather is; how if my feet and hands are cold, then I just can't get warm anywhere else. In fact, my extremities are so often freezing that I spend my life buying woollen bed socks and pairs of gloves that I inevitably lose.

I try so many different ways to get warm. I bury my hands deep in pockets. I buy extra-thick gloves, or lined ones, or ones that promise to 'banish cold hands for ever'. But there I still am - cold fingers, cold toes and miserable.

Lucy Cavendish

The Tootsie index: Lucy Cavendish tries a warm-up

My lack of warmth drives my husband mad. 'Do you have to have the heating on so high?' he'll say when he comes in of an evening to find me warming my feet and hands on the radiator.

In bed, things get even worse. I am for ever wanting to use him as a human hot-water bottle. As I try to tuck my feet into the warmth of his legs or back or whatever bit of his warm flesh that is nearest, he shudders and moves away. 'Get them off me!' he says.

I totally understand his hatred of my cold feet. Really, it is a curse. Even I hate them. All that palaver with thick tights and extra socks. I have taken to wearing tights under trousers but even that hasn't been enough with the recent snow. But it gets much worse than fashion dilemmas.

When my feet get cold, my toes cramp and I writhe around in pain. This has happened to me ever since I was a little girl and the only way I know for me to combat it is to wrench my toes slightly out and then hopefully they will eventually go back into their sockets. This involves me taking off my shoes and socks and tugging away, which is not possible on a packed train - which, nine times out of ten, is when it happens.

Feet and a heart shaped hot water bottle

Women have thinner skin than men, so their feet get colder quicker

So if my feet get cold and my toes become disjointed, I have to sit there with a painful grimace on my face, incapable of doing anything about it. But at least I now know I am not alone.

I had thought the reason my husband didn't feel the cold was because he's a Northerner and I'm a Southerner. However, it turns out it is much more to do with our physiognomy than where we originate from.

A new survey has found that women are nine times more likely to develop cold in their extremities than men. We are also more likely to suffer from Raynaud's disease - a recognised condition where not enough blood gets to the fingers and toes, causing extreme pain.

There are many theories as to why women suffer from this problem. Women have more evenly distributed fat layers, providing internal insulation. But while the result is that our blood supply favours protecting our core organs and trunk over our extremities, it means less blood flows to the hands and feet.

Men on the other hand have more heat-generating muscle mass, better supplied by blood vessels, increasing blood flow and, therefore, warmth.

Foot expert Margaret Dabbs says another reason why women's feet in particular get colder than men's is because our skin is thinner.

'The skin on our feet is thinner and has less subcutaneous fat than men's, so it is very hard for us to keep warm. You can see how women's faces get thinner as they get older, well, so does the skin on their feet and this is why the blood finds it hard to get to them and warm them up.

'People often come to my clinic complaining of extremely cold feet, but I find it usually only seriously affects women in the 40-plus age group as our skin gets thinner as we age.'

FEET FIRST

Avoid alcohol or caffeine as both increase blood flow to the skin, so while you might feel warmer, your body is losing heat

Dr Neetu Nirdosh, a doctor who specialises in anti-ageing, agrees. He says: 'It can certainly be to do with ageing as, once we get older, our once buoyant blood supply becomes limp. Blood no longer flows through our skin with a full dynamic force, and the consequence of this is distal hypothermia - cold extremities.

'The hands and feet are first to suffer as they contain a diffuse micro network of tiny capillaries which easily become damaged or blocked, and women feel this impact on a greater scale than men.

'Also, women can suffer from iron deficiency - anaemia - as they hold less iron in the body than men. Since iron is needed to transport oxygen around the blood, a lack will hamper blood flow.'

Apparently, the fact that some of us women seem to suffer from permanently cold feet can also be attributed to our hormones. Health advisor Nicola Stewart explains: 'Our circulation is linked to our hormonal system, and when we get a lack of iron in the thyroid we get cold as it is this that regulates our body temperature.'

She suggests a diet rich in pumpkin seeds, nuts, fish and watermelon to overcome the problem. So would a different diet help me? And is there anything else we women with cold hands and feet can actually do about it, bar eat sushi and seeds before we go to bed? Dr Nirdosh says there is.

'Lifestyle factors also massively accelerate age damage and weaken blood supply to the extremities,' he explains. 'With age, nutrients are not so well processed by the body.

'The combination of a poor diet which lacks vital vitamins and minerals such as B12 and folate, plus sleep deprivation, loss of muscle tissue due to inappropriate exercise and smoking all damage the blood supply.

'Extreme emotional instability and extreme cold conditions can obviously also cause cold extremities. But these are all things we can do something about.

HOT TIP

Mood can influence our temperature - people who are lonely or socially excluded feel the cold more

To take action against age-related body breakdown, you need to implement a proper nutritional plan high in dark green and dark red vegetables such as spinach and beetroot, complete protein sources like eggs and chicken, as well as daily supplementation with targeted vitamins and minerals, such as a complete vitamin B complex.

'Furthermore, to boost hormone activity and enhance muscle tissue, it's essential to exercise, and ensure you get six to eight hours sleep per night as this is when the body repairs itself.'

So, the answer is to eat iron-rich food, sleep more, exercise more and try to curtail those hormones. One blindingly obvious way to combat cold feet, I find, is to go to bed with a hot-water bottle. Men, though, tend to hate women having them. For a start, it makes the bed too hot for them.

There is also something slightly old lady-ish about going to bed with a fleece-covered water bottle. But, as I explain to my husband, it must be better for me to be sleeping peacefully than constantly shoving my cold feet into his back.

■ CHOOSE THE RIGHT SHOES

The circulatory system is the body’s own unique central heating system and the blood pumped around your body provides a kind of heat maintenance. So, if you wear tight shoes, this can cut off

the circulation to your feet, leaving them feeling cold.

■ WATCH WHAT YOU EAT

Vitamin K is important; it helps to strengthen the cardiac muscles in your heart as well as the blood capillaries. It also improves circulation around your body, including your feet, therefore keeping them warmer. Ginger, fish, parsley, salad, spring onions, apricots and celery are all good sources of Vitamin K.

■ EXERCISE REGULARLY

Regular exercise — whether it be a brisk walk, cycle or run — helps keep the heart healthy and strong, and so more efficient at pumping blood around the body.

■ USE A FOOT SPA

If you have very cold feet, it’s important not to warm them up too quickly, such as with a hot-water bottle or against a radiator — in the worst case scenario, you could end up with chilblains. The most effective way is bathing your feet in warm water or using a foot spa. This will warm up your feet slowly and naturally, and also keep them hydrated from the outside, improving circulation.

■ DRINK PLENTY OF WATER

When you are dehydrated your hands and feet get colder, too, as dry skin fails to maintain a good moisture balance and so does not retain heat.

■ WEAR NATURAL SOCKS

Cheap, synthetic, man-made fibres are so closely woven together that there are no air pockets in which to retain your natural body heat. Natural wool and cotton socks have more textured fibres and are less tightly bound, so they hold more warm air around the feet.

■ MOISTURISE

Lanolin, (available in cream form from Boots and Superdrug) helps to retain moisture in the skin, helping to improve blood flow and, therefore, retain heat.

Brucellosis Causes, Symptoms, Signs, Diagnosis, Treatment, History and Prevention

123What is brucellosis?

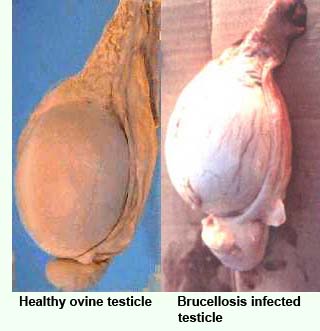
Brucellosis is an infectious disease caused by bacteria from the genus Brucella. It is an infection that affects mainly animals, including goats, sheep, camels, pigs, elk, deer, cattle, and dogs. Humans develop brucellosis when they come in contact with contaminated animals or animal products. The symptoms of brucellosis often resemble a flu-like illness.

Human brucellosis is a disease that is found worldwide, and it has an annual occurrence rate of more than 500,000 cases. Brucellosis tends to occur more commonly in regions with less established animal-disease-control programs and in areas where public-health initiatives may be less effective. High-risk areas include the Mediterranean Basin (Portugal, Spain, Southern France, Italy, Greece, Turkey, and North Africa), South and Central America, Eastern Europe, Africa, Asia, the Caribbean, and the Middle East. In the United States, brucellosis is much less common, with only 100-200 human cases reported each year. This decrease in cases in the United States is felt to be due to effective animal vaccination programs and milk pasteurization.

What is the history of brucellosis?

Brucellosis is a disease that is thought to have existed since ancient times, as it was first described more than 2,000 years ago by the Romans and Hippocrates. It was not until 1887 that a British physician, Dr .David Bruce, isolated the organism that causes brucellosis from several deceased patients from the island of Malta. This disease has had several names throughout its history, including Mediterranean fever, Malta fever, Crimean fever, Bang's disease, and undulant fever (because of the relapsing nature of the fever associated with the disease).

In the mid-20th century, the Brucella bacteria was also developed for use as a biological weapon by the United States. The use of brucellosis for biological warfare purposes was later banned in 1969 by President Nixon.


What causes brucellosis?

Brucellosis is a systemic infectious disease transmitted from certain animals to humans (zoonotic disease). Brucellosis in humans is predominantly caused by four different species of Brucella bacteria: Brucella melitensis (goats, sheep, camels), Brucella suis (pigs), Brucella abortus (cows, buffalo, elk, camels, yaks), and Brucella canis (dogs). Though all of these species can cause human brucellosis, Brucella melitensis is the most prevalent worldwide, and it is felt to cause the most severe cases of brucellosis.

How is brucellosis transmitted?

Brucellosis is transmitted from animals to humans in several ways. The most common route of transmission occurs when humans consume raw milk or cheese from infected sheep and goats. Infected animals shed the organism into their milk, and if humans eat or drink unpasteurized dairy products from these affected animals, they can develop brucellosis.

Brucellosis can also be transmitted to humans via inhalation of the organism or by direct contact with infected animal secretions. The bacteria can gain entry into the body through the inhalation of aerosolized secretions, through breaks in the skin, or through exposure of the mucous membranes/conjunctiva from the splashing of infected secretions. With these routes of entry, brucellosis is an occupational disease that can affect veterinarians, slaughterhouse workers, butchers, hunters, laboratory personnel, and those individuals who work closely with livestock (for example, farmers and shepherds).

Finally, an accidental injection with the livestock vaccine used against Brucella abortus can also lead to brucellosis in humans. Human-to-human transmission is very rare (via sexual contact and breastfeeding).

What are the symptoms and signs of brucellosis?

The symptoms and signs of brucellosis may develop from days to months after the initial exposure to the organism (incubation period). While some individuals may develop mild symptoms, others may go on to develop long-term chronic symptoms.

The signs and symptoms of brucellosis are extensive and they can be similar to many other febrile illnesses. They include

  • fever (the most common finding, and it may be intermittent and relapsing),


  • sweating,


  • body aches,


  • joint pain,


  • fatigue,


  • weakness,


  • dizziness,


  • headache,


  • depression,


  • irritability,


  • loss of appetite,


  • weight loss,


  • cough,


  • difficulty breathing,


  • chest pain,


  • abdominal pain,


  • enlarged liver and/or spleen.

Other symptoms and signs may also be present with brucellosis. Certain variables such as the severity of illness, the chronicity of illness, and the development of complications can all impact the clinical findings associated with the disease.

How is brucellosis diagnosed?

Making the diagnosis of brucellosis can sometimes be difficult because of the similar symptoms and signs shared with other febrile illnesses. An accurate history obtained by your health-care provider (including travel history, occupation, animal exposure, etc.) may be very helpful in raising the suspicion of brucellosis as a possible diagnosis.

In general, blood tests and blood/tissue cultures are necessary for making the diagnosis of brucellosis. Common blood tests used to make the diagnosis include testing for antibodies against the bacteria and isolating the organism from blood cultures. A biopsy of body tissue (from the bone marrow or the liver, for example) can also assist in making the diagnosis. Additional blood tests may demonstrate anemia, low platelets, a low white blood cell count, and elevated liver function tests.

Other imaging studies and procedures may also be performed initially depending on the individual's signs and symptoms. These tests may include CT scan, MRI, X-ray, ultrasound, lumbar puncture (spinal tap), joint aspiration, or an electrocardiogram (ECG).

What is the treatment for brucellosis?

The cornerstone of treatment for brucellosis is antibiotics. Because of the high relapse rate associated with the disease, the use of a multidrug (two or more) antibiotic regimen is recommended. The antimicrobials most commonly used include doxycycline (Vibramycin), streptomycin, rifampin (Rifadin), gentamicin (Garamycin), and trimethoprim-sulfamethoxazole (Bactrim, Septra). The combination of antibiotics used will vary based on disease severity, age and pregnancy.

In general, a full six-week course of antibiotics is recommended, and prompt treatment can lead to an improvement in symptoms and may also prevent the complications associated with brucellosis. However, relapse rates of the disease are still about 5%-10%, even with treatment. Depending on the severity of illness, the associated complications (if any) and the timing of treatment, recovery may take from a few weeks to a few months.

Rarely, surgical intervention may be needed for certain complications associated with brucellosis, such as abscess formation or heart-valve infection. Your health-care provider may need to consult other physicians, including surgeons, infectious disease specialists, or a neurologist.

What are the complications of brucellosis?

In general, if treated appropriately with antibiotics in a timely manner after the onset of symptoms, the prognosis for patients with brucellosis is excellent. The mortality rate is low (<2%).>

  • Bones and joints


    • Sacroiliitis, spondylitis, and osteomyelitis


  • Cardiovascular


    • Endocarditis (a primary cause of death), myocarditis, and pericarditis


  • Central nervous system (neurobrucellosis)


    • Meningoencephalitis


  • Gastrointestinal


    • Hepatitis, hepatic abscess, colitis, and spontaneous peritonitis


  • Genitourinary


    • Orchitis


  • Pulmonary


    • Pneumonia


  • Ocular


    • Optic neuritis and uveitis

How can brucellosis be prevented?

The prevention of brucellosis can be achieved through various measures. The most important step in preventing brucellosis in humans begins with the control and/or eradication of the infection in animals who serve as a reservoir. This requires a coordinated effort between local public-health organizations and animal-disease-control entities. The most effective measures to achieve this objective include animal vaccination programs, animal testing, and the elimination of infected animals. There is no human vaccine currently available.

In areas where eradication of the disease may not be possible, preventive measures are aimed at reducing the risk of transmission to humans. These measures may include

  • pasteurization of dairy products;


  • avoiding the consumption of unpasteurized dairy products, including milk and cheese;


  • avoiding the consumption of undercooked meat;


  • using appropriate barrier precautions (goggles, gloves, masks, etc) to avoid exposure to aerosols and body fluids for those with an occupational risk for brucellosis;


  • warning laboratory workers about potentially infected specimens so that appropriate biosafety level III precautions can be taken.
Brucellosis At A Glance
  • Brucellosis is an infectious disease caused by bacteria from the genus Brucella.
  • Brucellosis is an infection of certain animals that is transmitted to humans.
  • Humans acquire brucellosis when they come in contact with contaminated animals or animal products, most commonly from the ingestion of raw milk or cheese.
  • The symptoms of brucellosis may include fever, sweating, body aches, and joint pain.
  • Brucellosis is typically diagnosed through blood tests and by isolating the organism from blood and other body tissues.
  • A multidrug antibiotic regimen is the cornerstone of treatment for brucellosis.
  • The complications of brucellosis may involve various organ systems.
  • Brucellosis can be prevented by animal-disease-control measures, avoidance of unpasteurized dairy products, and occupational protective measures.

REFERENCES:

Al Nassir, Wafa, Michelle V. Lisgaris, Robert A. Salata. "Brucellosis." eMedicine. Feb. 3, 2009. .

Maloney Jr., Gerald E. "CBRNE-Brucellosis." eMedicine. Apr. 29, 2009. .

Switzerland. "Brucellosis (Human)." World Health Organization..

Switzerland. "Brucellosis." World Health Organization. .

United States. "Brucellosis." Centers for Disease Control and Prevention. Dec. 7, 2007. .

source


Yeast Infection Home Remedies-Natural Treatment

Yeast Infection Vaginal yeast infections can be both uncomfortable and embarrassing. Those who suffer from yeast infections will experience vaginal discharge which resembles cottage cheese, pain or discomfort during $exual intercourse or urination, itchiness, redness, and irritation. The good news is that you do not need to continue suffering from symptoms of a vaginal yeast infection. Here are some tips on how to get rid of a vaginal yeast infection naturally.

Yogurt

Yogurt is considered to be one of the most effective ways to get rid of yeast infections. It is recommended for you to use a tampon to insert plain yogurt into your vagina. The reason yogurt is known to be effective is because it contains a good bacteria which is known to ward off the yeast. While eating yogurt is believed to help get rid of the yeast infection, applying it directly to the skin is known to be much more effective. By eating yogurt on a daily basis, you will be able to reduce your chances of having the yeast infection reoccur in the future.

Garlic

Garlic is another home remedy which is known to be very effective at treating yeast infections. There are several ways to use garlic as a home remedy for yeast infections. The first is to insert a garlic clove into the vagina the same way that you would insert a tampon. Another home remedy for treating yeast infections that is known to be very effective is to use garlic paste. You can use a tampon to insert the garlic paste into the vagina.

Sugar

It is highly recommended for anyone who is suffering from a yeast infection to temporarily remove sugar from their diet. The reason is because sugar encourages the growth of yeast. It is recommended for yeast infection sufferers to eat more vegetables and fruits, as well as yogurt. Drinking more water, which can help cleanse the body, is also highly recommended.


Bacterial Vaginosis: Signs and Symptoms

Bacterial VaginosisBacterial vaginosis is a condition in which the vagina contains harmful bacteria. According to the Centers for Disease Control and Prevention, bacterial vaginosis is the most common vaginal infection among women of childbearing age. It is also known to be quite common among pregnant women. Although bacterial vaginosis can be caused by other factors aside from $ex, such as douching and smoking, it can be spread through $exual intercourse. Here are some of the common signs of bacterial vaginosis.


Vaginal Discharge

All women experience vaginal discharge at some point. If you notice that your vaginal discharge is a lot heavier than usual, this could be a sign of bacterial vaginosis. Most women who have bacterial vaginosis will have heavy white or gray vaginal discharge. Unlike with a yeast infection, it is usually thick in texture, rather than cottage cheese-like.

Foul Odor

Vaginal discharge may be foul in odor when you have bacterial vaginosis. This is why many women are known to experience a foul odor, especially after they have had $exual intercourse. Since the vagina produces a lot of natural lubrication at this point, discharge may increase and cause a foul odor.


Burning

One of the easiest to recognize symptoms of bacterial vaginosis is a burning or painful sensation. It will usually occur during $exual intercourse or urination. Many women with bacterial vaginosis notice this burning or pain periodically throughout the day at any time, however.
Itching

Many women with bacterial vaginosis experience some sort of itching. Itching may only be minimal, but for others it may be severe. Any time that you notice severe or persistent vaginal itching, it is important to get checked out by a doctor, however. This is a symptom which is experienced with many STDs.

Keep in mind that the symptoms of bacterial vaginosis are known to be very close to the symptoms that are experienced with certain STDs, such as chlamydia and gonorrhea. If you notice any of the symptoms of bacterial vaginosis listed above, it is important to visit a gynecologist.

Acai Berry to Lose Weight Should You Use?-Weight Loss Methods

Acai BerryThere has been a lot of talk recently about acai berry. The berry, which is known to offer a lot of health benefits, is believed to be a key component for effective weight loss. Many people are spending tons of money on acai berry diet supplements in hopes of losing weight. Will acai berry really work for you, however? Should you think about using it? Here are some of the things that you should know about acai berry before incorporating acai berry into your weight loss plan.


The Real Benefits of Acai Berry

It is important for you to be aware of what the real benefits of acai berry are. A lot of people are under the impression that acai berry will help you lose weight because it is an appetite suppressant. This is not true. Acai berry is known to cleanse or detoxify the body, which is why it is believed to be a great option for weight loss. Acai berry also is known to increase energy levels, helps regulate digestion, improves sleep routines, and may improve pain for arthritis sufferers.

Acai Berry Testimonials

There are many people who claim to have lost a lot weight by using acai berry. When reading any acai berry testimonial, it is important to be cautious of where it is coming from. If the testimonial that you are reading is on a website that is selling acai berry products, it is probably not entirely true. If you are reading testimonials on sources like Yahoo Answers or diet review websites, you may be able to believe them a bit more. Be sure to look for acai berry testimonials that include both the pros and cons.


Using Acai Berry Alone is Not Ideal

In order to lose weight, you should not believe that acai berry alone will do the trick. If you are going to try out an acai berry dietary supplement, the best thing that you can do is combine it with diet and exercise. Otherwise, it is unlikely that acai berry is going to work for you. Acai berry also may not provide you with the quick and effective results that you are hoping for. Taking an acai berry supplement may help boost energy levels and will cleanse your body, but it will not have an effect on your appetite.

It is ideal to be cautious when using any dietary supplement. Acai berry is unlikely to lead to long-term weight loss. Using acai berry in addition to a healthy diet and exercise is the best thing that you can do if you are interested in using it to lose weight.

source

Schizophrenia causes,symptoms,stages,diagnosis,treatment

WHAT IS SCHIZOPHRENIA?
What are the symptoms?
The symptoms of schizophrenia are divided into three categories:positive symptoms, disorganized symptoms, and negative symptoms.

Positive or psychotic symptoms of Schizophrenia:

• Delusions, unusual thoughts, and suspiciousness. People
with schizophrenia may have ideas that are strange, false,
and out of touch with reality. They may believe that people
are reading their thoughts or plotting against them, that others
are secretly monitoring and threatening them, or that
they can control other people’s minds or be controlled by
them.
http://www.clarian.org/ADAM/doc/graphics/images/en/17239.jpg

• Hallucinations. People with schizophrenia may hear voices
talking to them or about them, usually saying negative, critical,
or frightening things. Less commonly, the person may
see objects that don’t exist.
• Distorted perceptions. People with schizophrenia may have
a hard time making sense of everyday sights, sounds, smells,
tastes, and bodily sensations—so that ordinary things appear
frightening. They may be extra-sensitive to background
noises, lights, colors, and distractions.

Negative symptoms of Schizophrenia:
• Flat or blunted emotions. Schizophrenia can make it difficult
for people to experience feelings, know what they are
feeling, clearly express their emotions, or empathize with
other people’s feelings. It can be hard for people with such
symptoms to relate to others. This can lead to periods of intense
withdrawal and profound isolation.
• Lack of motivation or energy. People with schizophrenia usually
have trouble starting projects or finishing things they’ve
started. In extreme cases, they may have to be reminded to do
simple things like taking a bath or changing clothes.
• Lack of pleasure or interest in things. To people with
schizophrenia, the world seems flat, uninteresting, and cardboard.
It feels like it is not worth the effort to get out and do
things.
• Limited speech. People with schizophrenia often won’t say
much and may not speak unless spoken to.

Disorganized symptoms of Schizophrenia:
• Confused thinking and disorganized speech. People with
schizophrenia may have trouble thinking clearly and understanding
what other people say. It may be difficult for them
to carry on a conversation, plan ahead, and solve problems.
• Disorganized behavior. Schizophrenia can cause people to
do things that don’t make sense, repeat rhythmic gestures, or
make ritualistic movements. Sometimes the illness can cause
people to completely stop speaking or moving or to hold a
fixed position for long periods of time.
When does schizophrenia begin?
Schizophrenia can affect anyone at any age, but it usually
starts between adolescence and the age of 40. Children can also
be affected by schizophrenia, but this is rare.
The person who is having a first episode of schizophrenia may
have been ill for a long time before getting help. Usually he or
she comes to treatment because delusions or hallucinations have
triggered disturbing behavior. At this point, the person often
denies having a mental illness and does not want treatment. With
treatment, however, delusions and hallucinations are likely to get
much better. Most people make a good recovery from a first
episode of schizophrenia, although this can take several months.

What is the usual course of schizophrenia?

The severity of the course varies a lot and often depends on
whether the person keeps taking medicine. Patients can be divided
into three groups based on how severe their symptoms are
and how often they relapse.
The patient who has a mild course of illness and is
usually stable
• Takes medication as prescribed all the time
• Has had only one or two major relapses by age 45
• Has only a few mild symptoms

The patient who has a moderate course of illness and is often stable

• Takes medication as prescribed most of the time
• Has had several major relapses by age 45, plus periods of
increased symptoms during times of stress
• Has some persistent symptoms between relapses
The patient who has a severe and unstable course of illness
• Often doesn’t take medication as prescribed and may drop out
of treatment
• Relapses frequently and is stable only for short periods of
time between relapses
• Has a lot of bothersome symptoms
• Needs help with activities of daily living (e.g., finding a place
to live, managing money, cooking, laundry)
• Is likely to have other problems that make it harder to recover
(e.g., medical problems, substance abuse, or a mood disorder)

What are the stages of recovery?

• Acute episode: this is a period of very intense psychotic
symptoms. It may start suddenly or begin slowly over several
months.
• Stabilization after an acute episode: After the intense psychotic
symptoms are controlled by medication, there is usually
a period of troublesome, but much less severe, symptoms.
• Maintenance phase or between acute episodes: This is the
longer term recovery phase of the illness. The most intense
symptoms of the illness are controlled by medication, but
there may be some milder persistent symptoms. Many people
continue to improve during this phase, but at a slower pace.

Why is it important to diagnose and treat schizophrenia as early as possible?

Early diagnosis, proper treatment, and finding the right medications can help people in a number of important ways:
• Stabilize acute psychotic symptoms. The first priority is to
eliminate or reduce the positive (psychotic) symptoms, especially
when they are disruptive. Most people’s psychotic
symptoms can be stabilized within 6 weeks from the time they
start medication. Antipsychotic medications allow patients to
be discharged from the hospital much earlier.
• Reduce likelihood of relapse and rehospitalization. The more
relapses a person has, the harder it is to recover from them.
Proper treatment can prevent or delay relapse and break the
“revolving door” cycle.
• Ensure appropriate treatment. Sometimes a person is misdiagnosed
as having another disorder instead of schizophrenia.
This can be a serious problem because the person may end up
taking the wrong medications.
• Decrease alcohol/substance abuse. More than 50% of people
with schizophrenia have problems with alcohol or street drugs
at some point during their illness, and this makes matters
much worse. Prompt recognition and treatment of this “dual
diagnosis” problem is essential for recovery.
• Decrease risk of suicide. The overall lifetime rate of suicide
is over 10%. The risk is highest in the early years of the illness.
Fortunately, suicidal behavior is treatable, and the suicide
risk eventually decreases over time. Therefore, it is
very important to get professional help to avoid this tragic
outcome.
• Minimize problems in relationships and life disruption.
Early diagnosis and treatment decrease the risk that the illness
will get in the way of relationships and life goals.
• Reduce stress and burden on families. Schizophrenia places
a tremendous burden on families and loved ones. Programs
that involve families early in the treatment process reduce
relapse and decrease stress and disruption in the family.
• Begin rehabilitation. Early treatment allows the recovery
process to begin before long periods of disability have occurred.
Is schizophrenia inherited?
The answer is yes, but only to a degree. If no one in your
family has schizophrenia, the chances are only 1 in 100 that
you will have it. If one of your parents or a brother or a sister
has it, the chances go up, but only to about 10%. If both your
parents have schizophrenia, there is a 40% chance that you will
have it. If you have a family member with schizophrenia and
you have no signs of the illness by your 30s, it is extremely
unlikely that you will get this illness. If you have a parent or
brother or sister with schizophrenia, the chances of your children
getting schizophrenia are only slightly increased (only to
about 3%) and most genetic counselors do not consider this to
be a large enough difference to change one’s family planning.
Researchers have identified a number of genes that may be
linked to the disorder. This suggests that different kinds of
biochemical problems may lead to schizophrenia in different
people (just as there are different kinds of arthritis). However,
many other factors besides genetics are also involved. Research
is currently underway to identify these factors and learn
how they affect chances of developing the illness. We do know
that schizophrenia is not caused by bad parenting, trauma,
abuse, or personal weakness.

MEDICATION TREATMENT
The medications used to treat schizophrenia are called antipsychotics
because they help control the hallucinations, delusions,
and thinking problems associated with the illness.
Patients may need to try several different antipsychotic medications
before they find the medicine, or combination of medicines,
that works best for them. When the first antipsychotic
medication was introduced 50 years ago, this represented the
first effective treatment for schizophrenia. Three categories of
antipsychotics are now available, and the wide choice of
treatment options has greatly improved patients’ chances for
recovery.
Conventional antipsychotics
The antipsychotics in longest use are called conventional
antipsychotics. Although very effective, they often cause serious
or troublesome movement side effects.
Examples are:

  • Haldol (haloperidol)
  • Stelazine (trifluoperazine)
  • Mellaril (thioridazine)
  • Thorazine (chlorpromazine)
  • Navane (thiothixene)
  • Trilafon (perphenazine)
  • Prolixin (fluphenazine)
Conventional antipsychotics are becoming obsolete. Because
of side effects, experts usually recommend using a
newer atypical antipsychotic rather than a conventional.

There are two exceptions. For those individuals who are
already doing well on a conventional antipsychotic without
troublesome side effects, the experts recommend continuing it.
The other exception is when the person has had trouble taking
pills regularly. Two of the conventional antipsychotics, Prolixin
and Haldol, can be given in long-acting shots (called
“depot formulations”) at 2- to 4-week intervals. With depot
formulations, medication is stored in the body and slowly
released. No such depot preparations are yet available for the
newer antipsychotics.
Newer atypical antipsychotics
The treatment of schizophrenia has been revolutionized in
recent years by the introduction of several newer atypical antipsychotics.
These medications are called atypical because they
work in a different way than the conventional antipsychotics and
are much less likely to cause the distressing movement side
effects that can be so troubling with the conventional antipsychotics.
The following newer atypical antipsychotics are currently
available:
• Risperdal (risperidone)
• Seroquel (quetiapine)
• Zyprexa (olanzapine)
Other atypical antipsychotics, such as Zeldox (ziprasidone), may
be available in the near future.
The experts recommend the newer atypical medications as the
treatment of choice for most patients with schizophrenia.
Clozaril (clozapine)
Clozaril, introduced in 1990, was the first atypical antipsychotic.
Clozaril can help 25%–50% of patients who have not
responded to conventional antipsychotics. Unfortunately, Clozaril
has a rare but potentially very serious side effect. In fewer
than 1% of those taking it, Clozaril can decrease the number of
white blood cells necessary to fight infection. This means that
patients receiving Clozaril must have their blood checked regularly.
The experts recommend that Clozaril be used only after at
least two other safer antipsychotics have not worked.
Selecting medication for a first episode
The experts recommend the newer atypical antipsychotics as
the treatment of choice for a patient having a first episode of
schizophrenia. This reflects their better side effect profile and
lower risk of tardive dyskinesia. Clozapine is not recommended
for a first episode because of its side effects.
How long does it take antipsychotics to work?
Usually the antipsychotic medications take a while to begin
working. Before giving up on a medicine and switching to another
one, the experts recommend trying it for about 6 weeks
(and perhaps twice as long for Clozaril).

Selecting medication for relapses

If a person has a relapse because of not taking the medication
as prescribed, it is important to find out why he or she stopped
taking it. Sometimes people stop taking medication because of
troubling side effects. If this happens, the doctor may lower the
dose, add a side effect medication, or switch to a medication
with fewer side effects (usually an atypical antipsychotic). If the
person was not taking the medication for other reasons, the
doctor may suggest switching to a long-acting injection given
every 2–4 weeks, which makes it simpler to stay on the medication.
Sometimes a person will relapse despite taking the medication
as prescribed. This is generally a good reason to switch to another
medication—usually one of the newer atypical antipsychotics
if the person was taking a conventional antipsychotic, or
a different newer atypical antipsychotic if the person had already
tried an atypical antipsychotic. Fortunately, even if someone has
not responded well to a number of other antipsychotics, clozapine
is available as a backup and may work when other things
have failed.

Medication during the recovery period

We now know that schizophrenia is a highly treatable disease.
Like diabetes, a cure has not yet been found, but the symptoms
can be controlled with medication in most people. Prospects for
the future are constantly brighter through the pioneering explorations
in brain research and the development of many new
medications. To achieve good results, however, you must stick
to your treatment and avoid substance abuse.
It is very important that patients stay in treatment even after
recovery. Four out of five patients who stop taking their medications
after a first episode of schizophrenia will have a relapse.
The experts recommend that first episode patients stay on an
antipsychotic medication for 12–24 months before even trying to
reduce the dose. Patients who have had more than one episode of
schizophrenia or have not recovered fully from a first episode
will need treatment for a longer time, maybe even indefinitely.
Remember—stopping medication is the most frequent cause of
relapse and a more severe and unstable course of illness.
Be sure to take your medicine as directed. Even if you have
felt better for a long time, you can still have a relapse if you go
off your medication.

What are the possible side effects of antipsychotics?

Because people with schizophrenia have to take their medications
for a very long time, it is important to avoid and manage
unpleasant side effects.
Perhaps the biggest problem with the conventional antipsychotics
is that they often cause muscle movements or rigidity
called extrapyramidal side effects (EPS). People may feel
slowed down and stiff. Or they may be so restless that they have
to walk around all the time and feel like they’re jumping out of
their skin. The medicine can also cause tremors, especially in the
hands and feet. Sometimes the doctor will give a medication
called an anticholinergic (usually benztropine [Cogentin]) along
with the antipsychotic to prevent or treat EPS. The atypical
antipsychotics are much less likely to cause EPS than the conventional
antipsychotics.

When people take antipsychotic medications for a long time,
they sometimes develop a side effect called tardive dyskinesia—
uncontrolled movements of the mouth, a protruding tongue, or
facial grimaces. Hands and feet may move in a slow rhythmical
pattern without the person wishing this to happen and sometimes
even without the person being aware of it. The chances of developing
this side effect can be reduced by using the lowest possible
effective dose of antipsychotic medication. If someone
taking a conventional antipsychotic develops tardive dyskinesia,
the experts recommend switching to an atypical antipsychotic.

Medications for schizophrenia can cause problems with sexual
functioning that may make patients stop taking them. The doctor
will usually treat these problems by lowering the dose of antipsychotic
to the smallest effective dose or switching to a newer
atypical antipsychotic.
Weight gain can be a problem with all the antipsychotics, but
it is more common with the atypical antipsychotics than the
conventional antipsychotics. Diet and exercise can help.
A rare side effect of antipsychotic medications is neuroleptic
malignant syndrome, which involves very severe stiffness and
tremor that can lead to fever and other severe complications.
Such symptoms require the doctor’s immediate attention.
Tell your doctor right away about any side effects you have
Different people have different side effects, and some people
may have no problems at all with side effects. Also, what is a
troublesome side effect for one person (for example, sedation in
someone who already feels lethargic because of the illness) may
be a helpful effect for someone else (sedation in someone who
has trouble sleeping).
It can also be very hard to tell if a problem is part of the illness
or is a side effect of the medication. For example, conventional
antipsychotics can make you feel slowed down and
tired—but so can the lack of energy that is a negative symptom
of schizophrenia.
If you develop any new problem while taking an antipsychotic,
tell your doctor right away so that he can decide if it is
a side effect of your medication. If side effects are a problem
for you, you and your doctor can try a number of things to
help:
• Waiting a while to see if the side effect goes away on its own
• Reducing the amount of medicine
• Adding another medication to treat the side effect
• Trying a different medicine (especially an atypical antipsychotic)
to see if there are fewer or less bothersome side effects
Remember: Changing medicine is a complicated decision. It is
dangerous to make changes in your medicine on your own!
Changes in medication should also be made slowly.

PSYCHOSOCIAL TREATMENT
AND REHABILITATION

Although medication is almost always necessary in the
treatment of schizophrenia, it is not usually enough by itself.
People with schizophrenia also need services and support to
overcome the illness and to deal with the fear, isolation, and
stigma often associated with it. In the following sections, we
present the experts’ recommendations for the kinds of psychosocial
treatment, rehabilitation services, and living arrangements
that may be helpful at various stages of recovery. These
recommendations are intended to be guidelines, not rules. Each
patient is unique, and special circumstances may affect the
choice of which services are best for a specific patient at a
particular time during recovery. Also, some communities have
a lot of different services to choose from, while others unfortunately
have only a few. It is important for you to find out
what services are available to you in your community (and
when necessary to advocate for more).
Key components of psychosocial treatment
Patient and family education. Patient, family, and other key
people in the patient’s life need to learn as much as possible about
what schizophrenia is and how it is treated, and to develop the
knowledge and skills needed to avoid relapse and work toward
recovery. Patient and family education is an ongoing process that
is recommended throughout all phases of the illness.
Collaborative decision making. It is extremely important for
patient, family, and clinician to make decisions together about
treatments and goals to work toward. Joint decision making is
recommended at every stage of the illness. As patients recover,
they can take an increasingly active part in making decisions about
the management of their own illness.
Medication and symptom monitoring. Careful monitoring can
help ensure that patients take medication as prescribed and identify
early signs of relapse so that preventive steps can be taken. A
checklist of symptoms and side effects can be used to see how
well the medication is working, to check for signs of relapse, and
to figure out if efforts to decrease side effects are successful.
Medication can be monitored by helping the person fill a weekly
pill box or by providing supervision at medication times.
Assistance with obtaining medication. Paying for treatment is
often difficult. Health insurance coverage for psychiatric illnesses,
when available, may have high deductibles and copayments,
limited visits, or other restrictions that are not equal to the benefits
for other medical disorders. Public programs such as Medicaid and
Medicare may be available to finance treatment. The newer medications
that can be so helpful for most patients are unfortunately
more expensive than the older ones. The treatment team, patient,
and family should explore available ways to get access to the best
medication by working through public or private insurance,
copayment waivers, indigent drug programs, or drug company
compassionate need programs.
Assistance with obtaining services and resources. Patients often
need help obtaining services (such as psychiatric, medical, and
dental care) and help in applying for programs like disability
income and food stamps. Such assistance is especially important
for people having their first episode and for those who are more
severely ill.
Arrange for supervision of financial resources. Some patients
may need at least temporary help managing their finances—especially
those with a severe and unstable course of illness. If so, a
responsible person can be named as the patient’s “representative
payee.” Disability checks are then sent to the representative payee
who helps the patient pay bills, gives advice about spending, and
helps the patient avoid running out of money before the next check
comes.
Training and assistance with activities of daily living. Most
people who are recovering from schizophrenia want to become
more independent. Some people may need assistance learning
how to better manage everyday things like shopping, budgeting,
cooking, laundry, personal hygiene, and social/leisure
activities.

Supportive Therapy involves providing emotional support and
reassurance, reinforcing health-promoting behavior, and helping
the person accept and adjust to the illness and make the most of
his or her capabilities. Psychotherapy by itself is not effective in
treating schizophrenia. However, individual and group therapy
can provide important support, skill building, and friendship for
patients during the stabilization phase after an acute episode and
during the maintenance phase.
Peer support/self-help group. Almost all mutual support groups
are run by peers rather than professionals. Many of these groups
meet 1–4 times a month, depending on the needs and interest of
the members. Guest speakers are sometimes invited to add education
to the fellowship, caring, sharing, discussion, peer advice,
and mutual support that are vital parts of most consumer support
groups. Peer support/self-help groups can play a very important
role in the recovery process, especially when patients are stabilizing
after an acute episode and during long-term maintenance.

Types of services most often needed

Doctor and therapist appointments for medication management
and supportive therapy. It is very important to keep appointments
with your doctor and therapist during every phase of
the illness. These appointments are a necessary part of treatment
regardless of where you are in the recovery process—during an
acute episode, stabilizing after an acute episode, and during
long-term recovery and maintenance. It may be tempting to skip
appointments when your symptoms are under control, but continued
treatment during all phases of recovery is extremely
important in preventing relapse. Many people with schizophrenia
also need one or more of the services described below to
make the best recovery possible.
Assertive community treatment (ACT). Instead of patients going
to a mental health center, the ACT multidisciplinary team works
with them at home and in the community. ACT teams are staffed
to provide intensive services, so they can visit often—even every
day if needed. ACT teams help people with a lot of different
things like medication, money management, living arrangements,
problem solving, shopping, jobs, and school. ACT is a
long-term program that can continue to follow the person
through all phases of the illness. The experts strongly recommend
ACT programs, especially for patients who have a severe
and unstable course of illness.

Rehabilitation. Three types of rehabilitation programs may help
patients during the long-term recovery and maintenance phase of
the illness. Rehabilitation may be especially important for patients
who need to improve their job skills, want to work, have
worked in the past, and have few remaining symptoms.
• Psychosocial rehabilitation: a clubhouse program to help
people improve work skills with the goal of getting and
keeping a job. Fountain House and Thresholds are two wellknown
examples.
• Psychiatric rehabilitation: a program teaching skills that will
allow people to define and achieve personal goals regarding
work, education, socialization, and living arrangements.
• Vocational rehabilitation: a work assessment and training
program that is usually part of Vocational Rehabilitation
Services (VRS). This type of rehabilitation helps people prepare
for full-time competitive employment.
Intensive partial hospitalization. Patients in Partial Hospitalization
Programs (PHPs) typically attend structured groups for 4 to
6 hours a day, 3 to 5 days a week. These education, therapy, and
skill building groups are designed to help people avoid hospitalization
or get out of the hospital sooner, get symptoms under
control, and avoid a relapse. A PHP is usually recommended for
patients during acute episodes and while stabilizing after an
acute episode.

Aftercare day treatment. Day Treatment Programs (DTPs)
typically provide a place to go, a sense of belonging and friendship,
fun things to do, and a chance to learn and practice skills.
They also provide long-term support and an improved quality of
life. DTPs can help patients while they are stabilizing after an
acute episode and during long-term recovery and maintenance.
Case management. Case managers usually go out to see people
in their homes instead of making appointments at an office or
clinic. They can help people get the basic things they need such
as food, clothes, disability income, a place to live, and medical
treatment. They can also check to be sure patients are taking
their medication, help them manage money, take them grocery
shopping, and teach them skills so they can be more independent.
Having a case manager is helpful for many people with
schizophrenia.
Types of living arrangements
Treatment won’t work well if the person does not have a good
and stable place to live. A number of residential options have
been developed for patients with schizophrenia—unfortunately,
they are not all available in every community.
Brief respite/crisis home: an intensive residential program with
on-site nursing/clinical staff who provide 24-hour supervision,
structure, and treatment. This level of care can often help prevent
hospitalization for patients who are relapsing. Brief respite/
crisis homes can be a good choice for patients during acute
episodes and sometimes during the stabilization phase after an
acute episode.
Transitional group home: an intensive, structured program that
often includes in-house daily training in living skills and 24-hour
awake coverage by paraprofessionals. Treatment may be provided
in-house or the resident may attend a treatment or rehabilitation
program during the day. Transitional homes can help
patients while they are stabilizing after an acute episode and can
often serve as the next step after hospitalization or a brief respite/
crisis home. They can also be helpful during an acute relapse
if a brief respite/crisis home is not available.
Foster or boarding homes: supportive group living situation
owned and operated by lay people. Staff usually provide some
supervision and assistance during the day and a staff member
typically sleeps in the home at night. Foster homes and boarding
homes are recommended for patients during long-term recovery
and maintenance, especially if other options (living with family,
a supervised/supported apartment, or independent living) are not
available or do not fit patient/family needs and preferences.
Supervised or supported apartments: a building with several
one- or two-bedroom apartments, with needed support, assistance,
and supervision provided by a specially trained residential
manager who lives in one of the apartments or by periodic visits
from a mental health provider and/or family members. These
types of apartments are recommended for patients during longterm
recovery and maintenance.
Living with family: For some people, living with family may be
the best long-term arrangement. For others, this may be needed
only during acute episodes, especially if other types of residence
are not available or the patient and family prefer to live together.
Independent living: This type of living arrangement is strongly
recommended during long-term recovery and maintenance, but
may not be possible during acute episodes of the illness and for
patients with a more severe course of illness who may find it
hard to live independently.

OTHER TREATMENT ISSUES

Hospitalization
Patients who are acutely ill with schizophrenia may occasionally
require hospitalization to treat serious suicidal inclinations,
severe delusions, hallucinations, or disorganization and to prevent
injury to self or others. Hospitalizations usually last 1 to 2
weeks. However, longer hospitalization may be needed for first
episodes or if the person is slow to respond to treatment or has
other complications.
It is important for family members to be in touch with the
hospital staff so they can tell them what medications the person
has received in the past and what worked best. It is useful for the
family to be proactive in working with the staff to make living
and financial arrangements for the patient after discharge. Family
should ask the staff to give them information about the patient’s
illness and discuss ways to help the patient stick with
outpatient treatment.
After discharge
Patients are usually not fully recovered when they are discharged
from inpatient care. This can be a difficult time with
increased risks for relapse, substance abuse, and suicide. It is
important to be sure that a follow-up outpatient appointment
has been scheduled, ideally within a week after discharge, and
that the inpatient staff has provided the patient with enough
medication to last until that appointment. Ask the staff for an
around-the-clock phone number to call if there is a problem. It
is a good idea for someone to call the patient shortly before the
first appointment as a reminder. If the patient fails to show up,
everyone should work to make another appointment and to get
the person there for it. Good follow-up care is the best way to
avoid a severe course with repeated revolving-door hospitalizations.
Involuntary outpatient commitment
Involuntary outpatient commitment and “conditional release”
use a court order to require people to take medication
and stay in treatment in the community. While not a first line
treatment, resorting to legal pressure to require compliance
with treatment may sometimes be helpful for patients who
deny their illness and relapse frequently.

Postpsychotic depression

Depression is not uncommon during the maintenance
phase of treatment after the active psychotic symptoms have
resolved. It is important for patients and family members to
alert the treatment team if a patient who has been improving
develops depressive symptoms, since this can interfere with
the person’s recovery and increase the risk of suicide. The
doctor may suggest an antidepressant medication, which can
help relieve the depression. A psychiatric rehabilitation
program may benefit patients experiencing postpsychotic
depression who see little hope for the future. Family and
patient education can help everyone understand that
postpsychotic depression is just a part of the recovery process
and can be treated successfully. Peer self-help groups
may also provide valuable support for patients who have
postpsychotic depression.

Medical problems associated with schizophrenia

Patients with schizophrenia often get very inadequate care
for their medical illnesses. This is particularly unfortunate
because they are at increased risk for the complications of
smoking, obesity, hypertension, substance abuse, diabetes,
and cardiovascular problems. The experts therefore recommend
regular monitoring for medical illness and close collaboration
between the mental health clinicians and the
primary care doctor.
WHAT CAN I DO TO HELP MY DISORDER?
You and your family should learn as much as possible
about the disorder and its treatments. There are also a number
of other things you can do to help cope with the illness and
prevent relapses.

Avoid alcohol or illicit drugs

The use of these substances provides a short-term lift but
they have a devastating effect on the long-term course of the
illness. Programs to help control substance problems include
dual diagnosis treatment programs, group therapy, education,
or counseling. If you can’t stop using alcohol or substances,
you should still take your antipsychotic medication. Although
mixing the two is not a great idea, stopping the antipsychotic
medication is a much worse one.
Become familiar with early warning signs of a relapse
Each individual tends to have some “signature” signs that
warn of a coming episode. Some individuals may become
increasingly suspicious, worry that other people are talking
about them, have altered perceptions, become more irritable
or withdrawn, have trouble interacting with others or expressing
themselves clearly, or express bizarre ideas. Learn
to identify your own warning signals. When these signs
appear, speak to your doctor as soon as possible so that your
medications can be adjusted. Family members may also be
able to help you identify early warning signs of relapse.
Don’t quit your treatment
It is normal to have occasional doubts and discomfort with
treatment. Be sure to discuss your concerns and discomforts with
your doctor, therapist, and family. If you feel a medication is not
working or you are having trouble with side effects, tell your
doctor—don’t stop or adjust your medication on your own.
Symptoms that come back after stopping medication are sometimes
much harder to treat. Likewise, if you are not satisfied
with the program you are in, talk to your therapist about what
other services are available. With all the new treatment options,
you, your doctor, and your therapist can work together to find
the best and most comfortable program for you.

WHAT CAN FAMILIES AND FRIENDS DO TO HELP?

Once you find out that someone close to you has schizophrenia,
expect that it will have a profound impact on your life and
that you will need help in dealing with it. Because so many
people are afraid and uninformed about the disease, many families
try to hide it from friends and deal with it on their own. If
someone in your family has schizophrenia, you need understanding,
love, and support from others. No one causes schizophrenia,
just as no one causes diabetes, cancer, or heart disease.
You are not to blame—and you are not alone.

Help the person find appropriate treatment and the means to pay for it
The most important thing you can do is to help the person find
effective treatment and encourage him or her to stick with it. To
find a good doctor or clinic, contact your local mental health
center, ask your own physician for a referral, or contact the
psychiatry department of a university medical school or the
American Psychiatric Association. You can contact the National
Alliance for the Mentally Ill (NAMI) to consult with others who
have a family member with schizophrenia or who have the
disorder themselves.
It is also important to help the person find a way to pay for the
medications he or she needs. Social workers or case managers
may be able to help you through the difficult red tape, but you
may also have to contact your local Social Security or social
services office directly to find out what benefits are available in
your area and how to apply for them. Finding the way through
the maze of application processes is difficult even for those who
are not ill. A person with schizophrenia will certainly need your
help to obtain adequate benefits.

Learn about the disorder

If you are a family member or friend of someone with schizophrenia,
learn all you can about the illness and its treatment.
Don’t be shy about asking the doctor and therapist questions.
Read books and go to National Alliance for the Mentally Ill
(NAMI) meetings.
Encourage the person to stick with treatment
The most important factors in keeping patients out of the
hospital are for them to take their medications regularly and
avoid alcohol and street drugs. Work with your loved one to help
him or her remember to take the medicine. Long-acting injectable
forms of medication can help patients who find it hard to
take a pill every day.
Handling symptoms
Try your best to understand what your loved one is going
through and how the illness causes upsetting or difficult behavior.
When people are hallucinating or delusional, it’s
important to realize that the voices they hear and the images
they see are very real to them and difficult to ignore. You
should not argue with them, make fun of or criticize them, or
act alarmed.
After the acute episode has ended, it is a good time for the
patient, the family, and the healthcare provider to review what
has been learned about the person’s illness in a low-key and
non-blaming way. Everyone can work together to develop
plans for minimizing the problems and distress that future
episodes may cause. For example, the family members can
ask the person with schizophrenia to agree that, if they notice
warning signs of a relapse, it will be OK for them to contact
the doctor so that the medication can be adjusted to try to
prevent the relapse.

Learn the warning signs of suicide

Take any threats the person makes very seriously. Seek help
from the patient’s doctor and other family members and
friends. Call 911 or a hospital emergency room if the situation
becomes desperate. Encourage the person to realize that suicidal
thinking is a symptom of the illness and will pass in time
as the treatment takes effect. Always stress that the person’s
life is important to you and to others and that his or her suicide
would be a tremendous loss and burden to you, not a
relief.

Learn to recognize warning signs of relapse

Learn the warning signs of a relapse. Stay calm, acknowledge
how the person is feeling, indicate that it is a sign of a
return of the illness, suggest the importance of getting medical
help, and do what you can to help him or her feel safe and
more in control.
Don’t expect too fast a recovery
When people are recovering from an acute psychotic episode,
they need to approach life at their own pace. Don’t push
too hard. At the same time, don’t be too overprotective. Do
things with them, rather than for them, so they can regain their
sense of self-confidence. Help the person prioritize recovery
goals.
People with schizophrenia may have many health problems.
They often smoke a lot and may have poor nutrition and excessive
weight gain. Although you can encourage the patient
to try to control these problems, it is important not to put a lot
of pressure on him or her. Focus first on the most important
issues: medication adherence and avoiding alcohol and drug
use. Your top priority should be to help the patient avoid
relapse and maintain stability.

Handling crises

In some cases, behavior caused by schizophrenia can be
bizarre and threatening. If you are confronted with such behavior,
do your best to stay calm and nonjudgmental, be concise
and direct in whatever you say, clarify the reality of the
situation, and be clear about the limits of acceptable behavior.
Don’t feel that you have to handle the situation alone. Getmedical help. Your safety and the safety of the ill person
should always come first. When necessary, call the police or
911.
Coping with schizophrenia
Many people find that joining a family support group is a
turning point for them in their struggle to understand the illness
and get help for their relative and themselves. More than
1,000 such groups affiliated with the National Alliance for the
Mentally Ill (NAMI) are now active in local communities in all
50 states. Members of these groups share information and
strategies for everything from coping with symptoms to finding
financial, medical, and other resources.
Families who deal most successfully with a relative who has
schizophrenia are those who come to accept the illness and its
difficult consequences, develop realistic expectations for the ill
person and for themselves, accept all the help and support they
can get, and also keep a philosophical perspective and a sense
of humor. It takes times to develop these attitudes, but the
understanding support of others can be a great help.
Schizophrenia poses undeniable hardships for everyone in
the family. To deal with it in the best possible way, it’s particularly
important for you to take care of yourself, do things
you enjoy, and not allow the illness to consume your life.
Experts on schizophrenia believe that recently introduced new
treatments are already a big improvement and that new research
discoveries will bring a better understanding of schizophrenia
that will result in even more effective treatments. In
the meantime, help the patient live the best life he or she can
today, and do the same for yourself.
SUPPORT GROUPS
NAMI
The National Alliance for the Mentally Ill (NAMI) is the
national umbrella organization for more than 1,140 local support
and advocacy groups for families and individuals affected by
serious mental illnesses. To learn more about NAMI or locate
your state’s NAMI affiliate or office, contact:
NAMI
200 N. Glebe Rd., Suite 1015
Arlington, VA 22203-3754
NAMI Helpline at 800-950-NAMI (800-950-6264).
Several other organizations can also help you locate support
groups and information:
National Depressive and Manic-Depressive Association
730 N. Franklin St., Suite 501
Chicago IL, 60610-3526
800-82-NDMDA (800-826-3632)
National Mental Health Association (NMHA)
National Mental Health Information Center
1021 Prince Street
Alexandria, VA 22314-2971
800-969-6642
The National Mental Health Consumer Self Help Clearinghouse
1211 Chestnut St., 11th Floor
Philadelphia, PA 19107
800-688-4226
FOR MORE INFORMATION
The following materials provide more information on schizophrenia.
Most are available through NAMI. To order or to obtain
a complete publications list, write NAMI or call 703-524-7600.
Books
Adamec C. How to Live with a Mentally Ill Person: A Handbook
of Day-to-Day Strategies. Wiley & Sons, 1996.
Backlar P. The Family Face of Schizophrenia. J P Tarcher, 1994.
Bouricius JK. Psychoactive Drugs and Their Effects on Mentally
Ill Persons. NAMI, 1996.
Carter R, Golant SK. Helping Someone with Mental Illness.
Times Books, 1998.
Gorman JM. The New Psychiatry: The Essential Guide to Stateof-
the-Art Therapy, Medication, and Emotional Health. St.
Martins, 1996.
Hall L, Mark T. The Efficacy of Schizophrenia Treatment.
NAMI, 1995.
Hatfield A, Lefley HP. Surviving Mental Illness: Stress, Coping,
and Adaptation. Guilford, 1993.
Lefley HP. Family Caregiving in Mental Illness. Sage, 1996.
Mueser KT, Gingerich S. Coping with Schizophrenia: A Guide
for Families. Harbinger Press, 1994.
Torrey EF. Surviving Schizophrenia: For Families, Consumers,
and Providers (Third Edition). Harper & Row, 1995.
Weiden PJ. TeamCare Solutions. Eli Lilly, 1997 (to order, call
888-997-7392).
Weiden PJ, Diamond RJ, Scheifler PL, Ross R. Breakthroughs
in Antipsychotic Medications: A Guide for Consumers,
Families, and Clinicians. Norton, 1999.
Woolis R. When Someone You Love Has Mental Illness: A
Handbook for Family, Friends, and Caregivers.
Tarcher/Perigee, 1992.
Wyden P. Conquering Schizophrenia. Knopf, 1998.

Food Allergies-Could Hidden Food Allergies be Worsening ADHD in Children?

Could Hidden Food Allergies be Worsening ADHD in Children?
Increasing research involving children with ADHD is showing that some of these children are displaying marked improvement in their behavior and concentration with the elimination of certain foods from their diets. The studies are showing that these children are suffering from atypical food allergies.

These children do not necessarily present with a typical food allergy involving symptoms of hives, tingling throat and mouth, shortness of breath, swelling, or loss of consciousness. Often, in fact, their skin allergy tests and IgE blood tests can be normal or inconclusive.

However, a more recent blood test called IgG, which is a “delayed reaction” food allergy blood test can help determine if these children should be abstaining from certain foods. These delayed reactions to foods can take several hours to affect the children, and are sometimes referred to as hidden food allergies.

The main food culprits appear to be wheat, milk, eggs, chocolate, oranges and corn. This seems to be especially so for those children with ADHD who also suffer from migraines and arthritis.

It would appear that the brain could be affected by inflammatory reactions produced by the ingestion of certain foods in the digestive system. As the body detects the enemy food (allergen), it produces antibodies to fight them off. These antibodies flood the body with histamines, which activates the depletion of blood serum from the surrounding brain tissue. This results in the tiny blood capillaries which feed the brain having a diminished flow, causing the brain to lose its equilibrium. From a psychological guide, indicators of this include cognitive and attention dysfunction, and memory loss.

These types of food allergy sensitivities can take up to several hours to present themselves, so the use of a food diary can be helpful to monitor the intake of food and the resulting behavior. Over a period of a month or so, it may become apparent which foods are unbalancing your child.

If you suspect that your child’s ADHD is triggered by certain foods, and that they could have a hidden food allergy, why not visit this website for further helpful information and products?

Diet Pills-dietary supplement-weight loss diets

It's Time to Know Your Diet Pill

It would be wise to ask yourself all questions about your diet pill before actually using them. Ask them or those who can provide you with the information you might need in selecting which one would be best for you. Ask the producers or manufacturers of the pills themselves so that they can provide you with relevant information in deciding whether or not to try out their product.


Now you might ask yourself, “Aren’t these warnings excessive for an over-the-counter pill?” After all, the side effects, if there are any, are minimal, the instructions are easy. And should I later on decide not to, I could always discontinue their use.

Weight loss pill

http://yourvancouverpersonaltrainer.com/blog/wp-content/uploads/2009/05/dietpills.jpg

In the first place, remember that even the advertisements of slimming pill contain warnings or cautions against fake or inauthentic pills on the market. That the players in the industry themselves recognize the proliferation of other potentially dangerous products should already, at the very least, keep you on your toes.

Secondly, anybody seriously considering a successful weight loss program should formulate their plan carefully. It would help the individual tremendously if the very first pill he or she takes – after the appropriate pre-research – justifies their reasonable expectations of the product. It would not only be the resulting weight loss that would be of great benefit, but also the confidence that there are good and reliable products out there that you can rely on. After all, many consumers try a product, don’t like it, and decide never to try again. This can significantly reduce the opportunities offered them by the more reliable products.

Diet Pill

http://static.howstuffworks.com/gif/diet-pill-2.jpg

Be a Smart Consumer

Researching beforehand can also keep your expectations reasonable. We’ve all seen those advertisements guaranteeing a better life and greater health and happiness after you use their product. There are those that absolutely guarantee effective weight loss and a better life and call upon you to make the life changing decision by purchasing their product.

Now, you can choose to believe those banner advertisements, or you can choose to believe the information you’ve gathered by independently relevant means. In this manner, you can winnow out those “fad” products and make rational choices.

And in keeping your expectations reasonable, it would be prudent to know what it is that your product can and cannot do. If it can help you lose a substantial amount of weight, does it also help keep them off? Most products only guarantee short term benefits of course, and thereafter recommend their use in conjunction with other weight management measures such as proper diet and exercise in order to keep them off. Losing even just a few pounds can already be a tremendous benefit, and can jumpstart other lifestyle health changes that all together will lead to greater health and happiness.

Finally, look at the side effects and contraindications. This is in keeping with your expectations reasonable. “Know what to expect”. Some products will give you an increased or different kind of bowel movement. There are those that will result in a severely decreased appetite that might come back with a vengeance should you discontinue taking the diet pills, unless you took the initiative in looking to your food intake in the meantime. Some products might result in periods of drowsiness, or temporary sleepiness, in much the same way as we take other over-the-counter medicine.

Acai berry health benefits-acai weight loss-lose weight-health

Acai berries weight loss!
The small purple round berries that look similar to a blueberry grow wild in the Amazon Rainforest on the acai palm tree. The acai berry was a well kept secret of the natives living along the Amazon River until about 5 years ago when it was discovered and marketed in the American market.


The acai berry is rich in antioxidants, 10x more than that of grapes and twice the amount found in a blueberry. The antioxidants promote better health by reducing the free radicals in your body and this in turn slows and sometimes can prevent the process of aging.

best weight loss
http://www.dietplusexercise.com/templates/dpe1/images/slim-girl.png

The many health benefits of the acai berry is the increased energy and stamina, fighting off heart disease, improving cholesterol, stabilizing blood sugar levels, inducing better sleep, and supplying you with a huge amount of healthy nutrients and vitamins. The list for the benefits of the acai berry can go on forever, with the amount of nutrients found inside it is no wonder that the market has been flooded with the energy drinks, supplements, and juices made form the acai berry.

Antioxidant

https://blogger.googleusercontent.com/img/b/R29vZ2xl/AVvXsEi2fQk7cS4N58Q3qR5utQ3PXGbyUC8wq6ewDfxuyODfFva0FaCg1PoDIkipI5PBoONVoIVp1_rujMB7Kkt3pwwURyym5vH7gTHgP7-F4YFKLLhXq4G5nfkKiXdXPNnBCJE-Hap6RhyphenhyphenzeBM/s320/antioxidants_fruit_Juice_dr.jpg

The flavorful little berries are tropical in taste and very pleasant. The deep purple fruit contains 90% seed and only 10% pulp, so harvesting them and making use of them can be a tedious process. There is no downside to the benefits, they come naturally are safe, effective, and proven to work. Other Acai Berry Benefits are that it is 100% effective, 100% natural, and has 0% negative effects. Anyone who consumes the Acai Berry will experience a feeling of wellness, increased appetite and "slimmer" appearance.

Diet pregnancy-What should be your Diet during Pregnancy ?

A pregnant woman needs up to 300 more food calories a day than she used to when she was not pregnant, as well as more vitamins, minerals, folic acid and iron. Such nutrients help forming strong bones, skin and teeth in the baby.

To make sure you ingest the right protein and vitamin rich foods, keep the following on your weekly list: fish, meat and poultry, cheese, yoghurt and milk, beans, peas and eggs.


Spinach and leafy green vegetables, broccoli, asparagus, strawberries and tomatoes, as well as cereals, are a good source of folic acid.

Pregnant Women

http://www.publishersweekly.com/articles/blog/880000288/20071212/Pregnant_woman.jpg

Iron is contained in red meat, fish and chicken, liver and kidneys, green vegetables, beans, fortified cereals as well as whole-grain bread.

The secret is eating a wide variety of foods of the kind mentioned above, because every single food on the list will contribute to your and your baby’s health by providing one or more essential nutrients.

If the doctor advises, when the necessary quantity of nutrients is not assimilated by simply eating these foods, a pregnant woman can take dietary supplements, but only under a specialist’s supervision.

pregnant-woman-food

http://mirror-us-ga1.gallery.hd.org/_exhibits/people/pregnant-woman-food-and-drink-2-AJHD.jpg

There are also substances that are to be avoided completely under the circumstances. Drugs, alcoholic drinks and tobacco are top of the list. Even medicines must be checked because most of them are known to give side effects. A pregnant woman should not treat herself at home, not even for ordinary flu. What seems harmless to her may damage the baby.

Coffee should be limited to one or two cups a day. All foods should be very well cooked before eating. Special attention ought to be paid to meat, fish, shellfish and eggs, as well as types of cheese which have not been pasteurized. Even fresh fruit and vegetables can be dangerous as they may be a source of bacteria.

Rheumatoid arthritis-Symptoms--Causes-Treatments

Rheumatoid arthritis often starts in young adults and flares up in middle age. The condition is more common in women than in men. The causes of rheumatoid arthritis are complex and not perfectly understood.


Rheumatoid arthritis (RA) is an inflammatory autoimmune disease that is characterized by the destruction of joint cartilage and inflammation of the synovium (joint fluid) (Abbas et al., 1994). The joints of the extremities, particularly the metacarpophalangeal, interphalangeal, and wrist joints, are the primary diseased sites, but as the disease progresses, the larger joints, especially the knees, can also be affected. The disease is an inflammatory arthritis that involves stiffness, pain, swelling, and erythema. As the disease progresses, osteoporosis of the contiguous bone, destruction of joint cartilage, bone resorption, and displacement by ankylosis occur. Subcutaneous nodules may also form at pressure points, particularly on the anterior side of the forearms, in 15-20% of reported cases. Systemic complications include damage to various organs (lungs, pleura, pericardium, myocardium, eyes, and central nervous system) due to inflammatory reactions. The outcome of the disease varies among patients, ranging from complete recovery to total incapacitation within years of the onset of the disease. In the most severe cases, vasculitis may occur. Women represent 75% of the reported cases of RA. There are two major peaks of incidence with regard to age: one between 30 and 40 years and one between 50 and 60 years (Bach, 1982).

Early experimental work focused on the importance of B-cells in the pathology of RA. Later interest has focused on T-cells. Observations that RA is strongly associated with certain MHC (major histocompatibility complex) alleles and that activated T-cells are found in affected joints have indicated that much focus should be given to cell-mediated immune responses. Whether activated T-cells initially respond to a microbial antigen, superantigen, or self-constituent is unclear to date (Chini et al., 2002).


http://www.topnews.in/health/files/angela2.jpg

Immunology and the Causes of RA
The development of lesions in rheumatoid arthritis appears to include both cell-mediated and humoral responses. Early research aimed at identifying the cells present in the inflamed synovium, and it has been concluded that CD4+ T-cells, activated B-lymphocytes, and plasma cells, as well as well-formed lymphoid follicles with germinal centers (in more severe cases), are present in the synovium of patients diagnosed with RA (Abbas et al., 1994). T-cells are the dominant cell type in the synovial filtrate of patients with RA, and there is at least a partial therapeutic effect of T-cell depletion for these patients (Berner et al., 2000). Current understanding of RA suggests that TH1 cells that are specific for a particular antigen (which has yet to be identified) are present in the joints of people with RA. This antigen activates T-cells to release lymphokines that cause local inflammation at the joints. The clinical manifestations of this inflammation include swelling, accumulation of polymorphonuclear leukocytes and macrophages at the site of inflammation, cartilage damage, and, thus, destruction of the joint (Janeway et al., 2001).

T-cells are the dominant type of cell that infiltrates the synovial membrane in RA. In many patients, the lymphocytes that infiltrate the tissues are organized into follicles that are structurally similar to germinal centers, which strongly supports the idea that RA is an antigen-driven immune response. Recent studies, however, have focused on the possibility that T-cells have an alternative role besides antigen recognition in the joints. Irregularities are found in the global and synovial T-cell receptor (TCR) repertoire of RA patients. The T-cell repertoire shows an emergence of clonal T-cell populations. CD4 T-cell clones are present uniformly in circulation and infiltrate into synovial lesions. CD8 T-cells clones are also found in patients with RA; although these clones are not limited to RA patients, they are larger and more frequent in people with the disease. CD4 T-cells are autoreactive to ubiquitous antigen, do not express the CD28 molecule, and do not require costimulatory signals to secrete cytokines. A study performed at the Mayo Clinic in 2002 found that RA is associated with a generalized defect in diversity maintenance of the TCR repertoire. This results in clonal expression of peripheral T-cells and repertoire contraction. Of significance, the researchers found that these irregularities involve memory and naïve T-cells, which suggests that the abnormality is a defect in T-cell homeostasis, rather than a consequence of antigen-recognition in the synovium. Specifically, the study showed that the CD4 TCR beta-chain diversity is limited in RA patients. Loss in diversity leads to the insufficient influx of ‘novel’ T-cells. Peripheral T-cells respond by replicating vigorously to compensate for the loss of new production, and clonal populations are formed. The multiclonal T-cells proliferation and the associated repertoire contraction have important implications for the course of the disease. It appears that the T-cell clones recognize a ubiquitously distributed autoantigen in RA patients. A recent study by Kouskoff et al. describes that transgenic mice expressing a TCR that recognizes self-MHC molecules develops arthritis that resembles RA but no other autoimmune diseases. To date, however, the autoantigen remains to be elucidated (Wagner et al., 1998).

Unusual distortions of the naïve T-cell repertoire have also been examined. These defects have led researchers to conclude that abnormal T-cell development and differentiation occurs in RA; autoimmunity could be caused by the inappropriate development and maturation of T-cells. RA patients appear to have fewer naïve T-cells with atypical phenotypes as compared to controls; these data suggest abnormal T-cell proliferation and phenotypic differentiation occur in response to inflammatory stimuli in patients with RA. These atypical cells appear to have a reduced threshold for activation and may bypass lymph nodes in favor of peripheral sites, which, during an infection, can lead to autoreactivity (Ponchel et al., 2002). Following this line of thought, hyperfunctioning T-cells could secrete local mediators in the synovial fluid, leading to arthritis. This hypothesis is supported by the fact that numerous T cells are found in the synovium of affected individuals. Also, injection of T-cell culture supernatants can induce inflammatory arthritis that resembles the clinical manifestations of RA. In this scenario, immune complex formation may be caused by T-cell hyperfunction through a helper effect, and the immune complexes would cause certain symptoms, including nodules and vasculitis (Bach, 1982).

Fig. 2 The Pathogenesis of Rheumatoid Arthritis. The development of lesions in rheumatoid arthritis appears to include both cell-mediated and humoral responses. CD4+ T-cells, activated B-lymphocytes, and plasma cells, as well as well-formed lymphoid follicles with germinal centers (in more severe cases), are present in the synovium of patients diagnosed with RA. T-cells are the dominant cell type in the synovial filtrate of patients with RA. Cytokine secretion by activated T-cells leads to an inflamed synovium and the formation of pannus (Abbas et al., 1994).


http://www.arxmanhealth.com/wp-content/uploads/2008/11/rheumatoid_arthritis.jpg

Treatments
Anti-TNF-alpha Treatments
Cytokines are protein mediators that are implicated in nearly all biological processes, including cell growth, differentiation, inflammation, and immunity. In patients with RA, nearly all cytokines are expressed in RA tissue in a continuous fashion. Researchers previously thought that targeting the blockade of a particular cytokine would be an ineffective therapeutic treatment since, they supposed, other cytokines would take over the role of the blocked cytokine. Research with RA has led them to a different hypothesis. IL-1 has been shown to induce the destruction of cartilage and bone, and five signals present in the RA synovium (IFN-gamma, GM-CSF, TNF-alpha, immune complexes, and IL-1 itself) help to regulate IL-1 production. However, a study done at the Kennedy Institute of Rheumatology found that blocking TNF-alpha abolished IL-1 bioactivity. Anti-TNF antibodies were also found to downregulate GM-CSF, IL-6, and IL-8. Researchers determined that pro-inflammatory cytokines are co-regulated, and the key inflammatory cytokines are TNF-alpha and IL-2. This led the way for the development of anti-TNF-alpha treatments; both soluble-receptor antagonists and cytokine antibodies have been developed as anti-TNF-alpha therapies (Feldmann et al., 1999).

Medications Commonly Used to Treat Rheumatoid Arthritis (Rang et al., 1995)
Four types are medications are commonly used to treat rheumatoid arthritis. These include aspirin and other nonsteroidal anti-inflammatory drugs (NSAIDs), disease-modifying antirheumatic drugs (DMARDs), immuno-suppressants, and corticosteroids (glucocorticoids).

NSAIDs have three major types of effect. They are anti-inflammatory agents; they have an analgesic effect (reduction of pain); and they have an antipyretic effect (lowering of raised temperature). Examples of these drugs include, but are not limited to, plain aspirin, buffered aspirin, ibuprofen (Advil ®, Motrin IB ®), ketoprofen (Orudis®), naproxen (Naprosyn®), celecoxib (Celebrex®), and rofecoxiv (Vioxx®).
Anti-inflammatory effects: The primary action of the drugs is to inhibit arachidonate cyclo-oxygenase and, thus, to inhibit the production of prostaglandins and thromboxanes. One type of cyclo-oxygenase, COX-2, is induced in activated inflammatory cells and is the enzyme that produces the prostanoid inflammatory mediators. NSAIDs reduce the components of inflammation that are caused by COX-2 action, which include vasodilation, edema, and pain. These drugs have no effect on the processes that contribute to tissue destruction in RA; they simply reduce the generation of toxic O2 products and inhibit lymphocyte activation.
Antipyretic effects: NSAIDs inhibit prostaglandin production in the hypothalamus. During an inflammatory reaction, macrophages release IL-1, which stimulates the generation of E-type prostaglandins in the hypothalamus, which elevate the body temperature of the individual. NSAIDs, thus, act to reduce body temperature when it is raised above normal levels.
Analgesic effects: NSAIDs are effective against pain that is caused by prostaglandins acting on nociceptors (ie. pain associated with inflammation or tissue damage). Decreased prostaglandin production leads to less sensitization of nociceptic nerve endings to the inflammatory mediators, bradykinin and 5-hydroxytryptamine (Rang et al., 1995).

DMARDs are distinct from NSAIDs in that they do more than simply alleviate the symptoms of RA. They are used to alter the course of the disease and prevent joint and cartilage destruction. Three types of DMARDs are widely used; these include gold compounds (Myochrysine®, Ridaura®), penicillamine (Cuprimine®, Depen®), and chloroquine (Plaquenil®). Although their mechanisms of action have not been fully elucidated, their effects have had a profound effect on RA patients.
Gold Compounds: Gold compounds help to stop the progression of bone and joint damage in RA. Pain and joint swelling are reduced when these drugs help to reduce the concentration of rheumatoid factor. Although the exact mechanism of action is not fully understood, any or all of the following effects can contribute to the mechanism: inhibition of mitogen-induced lymphocyte proliferation, reduction of lysosomal enzymes, reduction in the production of toxic O2 metabolites from phagocytes, inhibition of chemotaxis of neutrophils, and reduction in IL-2 production.
Penicillamine: Penicillamine prevents the maturation of newly synthesized collagen. Although the mechanism of action is not fully understood, it has been observed that joint swelling subsides, nodules disappear, and IL-1 production is reduced. About 75% of patients with RA respond to this treatment.
Chloroquine: Anti-malarial drugs cause remission of RA but do not stop bone destruction. They inhibit mitogen-induced lymphocyte proliferation and decrease leukocyte chemotaxis. They also reduce IL-1 production (Rang et al., 1995)

Immuno-suppressants, which are considered DMARDs, restrain an overly-active immune system. These drugs include cyclosporine (Sandimmune®, Neoral®) and cytotoxic agents such as azathioprene (Imuran®).
Cyclosporine: Cyclosporine suppresses both cell-mediated and humoral responses. It acts on T-lymphocytes at the induction stage to stop clonal proliferation. The transduction pathway for lymphokine synthesis is inhibited, mainly the production of IL-2. It also inhibits IL-2 receptor expression on T-cells that respond to IL-2. The induction of cytotoxic T-cells is also inhibited. B-cell responses are suppressed because lymphokine synthesis and secretion from activated T-cells is inhibited.
Azathioprine: Azathioprine is metabolized to give mercaptiopurine, which is a purine analogue that inhibits DNA synthesis. This drug depresses both cell-mediated and humoral responses since it inhibits clonal proliferation by a cytotoxic action on dividing cells (Rang et al., 1995).

Corticosteroids have anti-inflammatory and immunosuppressive effects. They include prednisone (Deltasone®, Orasone®), hydrocortisone, dexamethasone, and methylprednisolone (Medrol®). These drugs reduce vasodilation and decrease fluid exudation. In areas of acute inflammation, they decrease the number and activity of leukocytes (decreased action of T-helper cells and reduced clonal proliferation of T-cells due to decreased production of IL-2; decreased release of monocytes and increased number of neutrophils from the bone marrow). In areas of chronic inflammation, the activity of mononuclear cells is decreased. In lymphoid areas, there is decreased clonal expansion of T- and B-cells and decreased action of cytokine-secreting T-cells. These drugs decrease the production of many cytokines, including IL-1, IL-2, IL-3, IL-4, IL-5, Il-6, IL-8, TNF-alpha, and GM-CSF. They also help to decrease the complement component in the blood. Overall, they reduce chronic inflammation and autoimmune reactions. Glucocorticoids act by interacting with intracellular receptors; the steroid-receptor complex interacts with DNA to modify gene transcription. These drugs perform their anti-inflammatory and immunosuppressive actions as follows: inhibition of transcription of the gene for COX-2; blockage of vitamin-D3-mediated induction of the osteocalcin gene in osteoclasts and modification of the transcription of the collagenase gene; and increased synthesis of an anti-inflammatory mediator protein (lipocortin 1) which inhibits phospholipase A2 and blocks the production of platelet-activating factor (Rang et al., 1995).


Paste Not Allowed